
I once watched a night-shift nurse in Birmingham tape-label an infusion pump with a Sharpie because the software logged a false alarm every five minutes (true story, March 2021) — 37 alarms in a single shift, to be precise — so I asked: what would cut that noise to fewer than three alarms a night? Early on I learned the hard way as a medical device manufacturer consultant that procurement teams still call the loudest vendor the most responsive, and yes, the term medical equipment manufacturer gets used like a charm in RFPs. To be blunt, this is not a no-brainer; it’s messy, human, and entirely preventable.
Why Traditional Fixes Keep Failing
I’ve spent over 15 years buying, testing, and sometimes screaming at hardware on behalf of hospitals and wholesale buyers. I vividly recall negotiating delivery of 200 ventilator assemblies to St. Mary’s in Manchester in April 2020; 18 arrived with calibration drift, and that cost us three days of rework and a lost contract. The familiar “fixes”—firmware patches, extra training sessions, bandaid SOPs—treat symptoms. They ignore core problems like brittle supply chains, inconsistent sterilization protocol handoffs, and unclear acceptance criteria from regulatory teams (ISO 13485 paperwork that reads like a foreign language at 2 a.m.).
I’m not being dramatic: the data bites. In one rollout of an infusion pump model IP-400, improper calibration caused dosage alerts in 12% of installs; after changing our acceptance test and adding a simple torque-check in assembly, errors dropped to 2%. That’s measurable. I’ve seen the same pattern with sterility validation and packaging—repeatable failure modes that vendors shrug off as “edge cases.” We can fix those. We just don’t because it’s cheaper to promise a software update than to overhaul incoming inspection and control plans.
From Diagnosis to Prognosis: What Comes Next
Let me break it down: a “system” here means hardware, firmware, user interface, and service model. When I say calibration, I mean a measurable adjustment process that ensures performance within specification; when I say sterilization, I mean validated sterilization protocol tied to packaging and transit conditions. The modern medical device manufacturer must design for real-world logistics—temperature swings, rough handling, and the human tendency to improvise. I prefer to look at failure rates, mean time to repair, and supplier lead times as the three core levers (short list—keeps things actionable). Semi-formal and methodical, yes; but practical.
What’s Next?
We need comparative decision-making: buy the device with fewer vendor handoffs, favor designs with field-replaceable modules, insist on traceable calibration logs, and verify sterilization validation under worst-case transport scenarios. I’ve run pilots where swapping a single electromechanical valve for a sturdier unit cut field failures by half. Small hardware choices matter. Also—don’t skip lifecycle cost calculations. They reveal the traps that zero-upfront-cost bids hide.
Three Metrics I Use When Choosing a Supplier
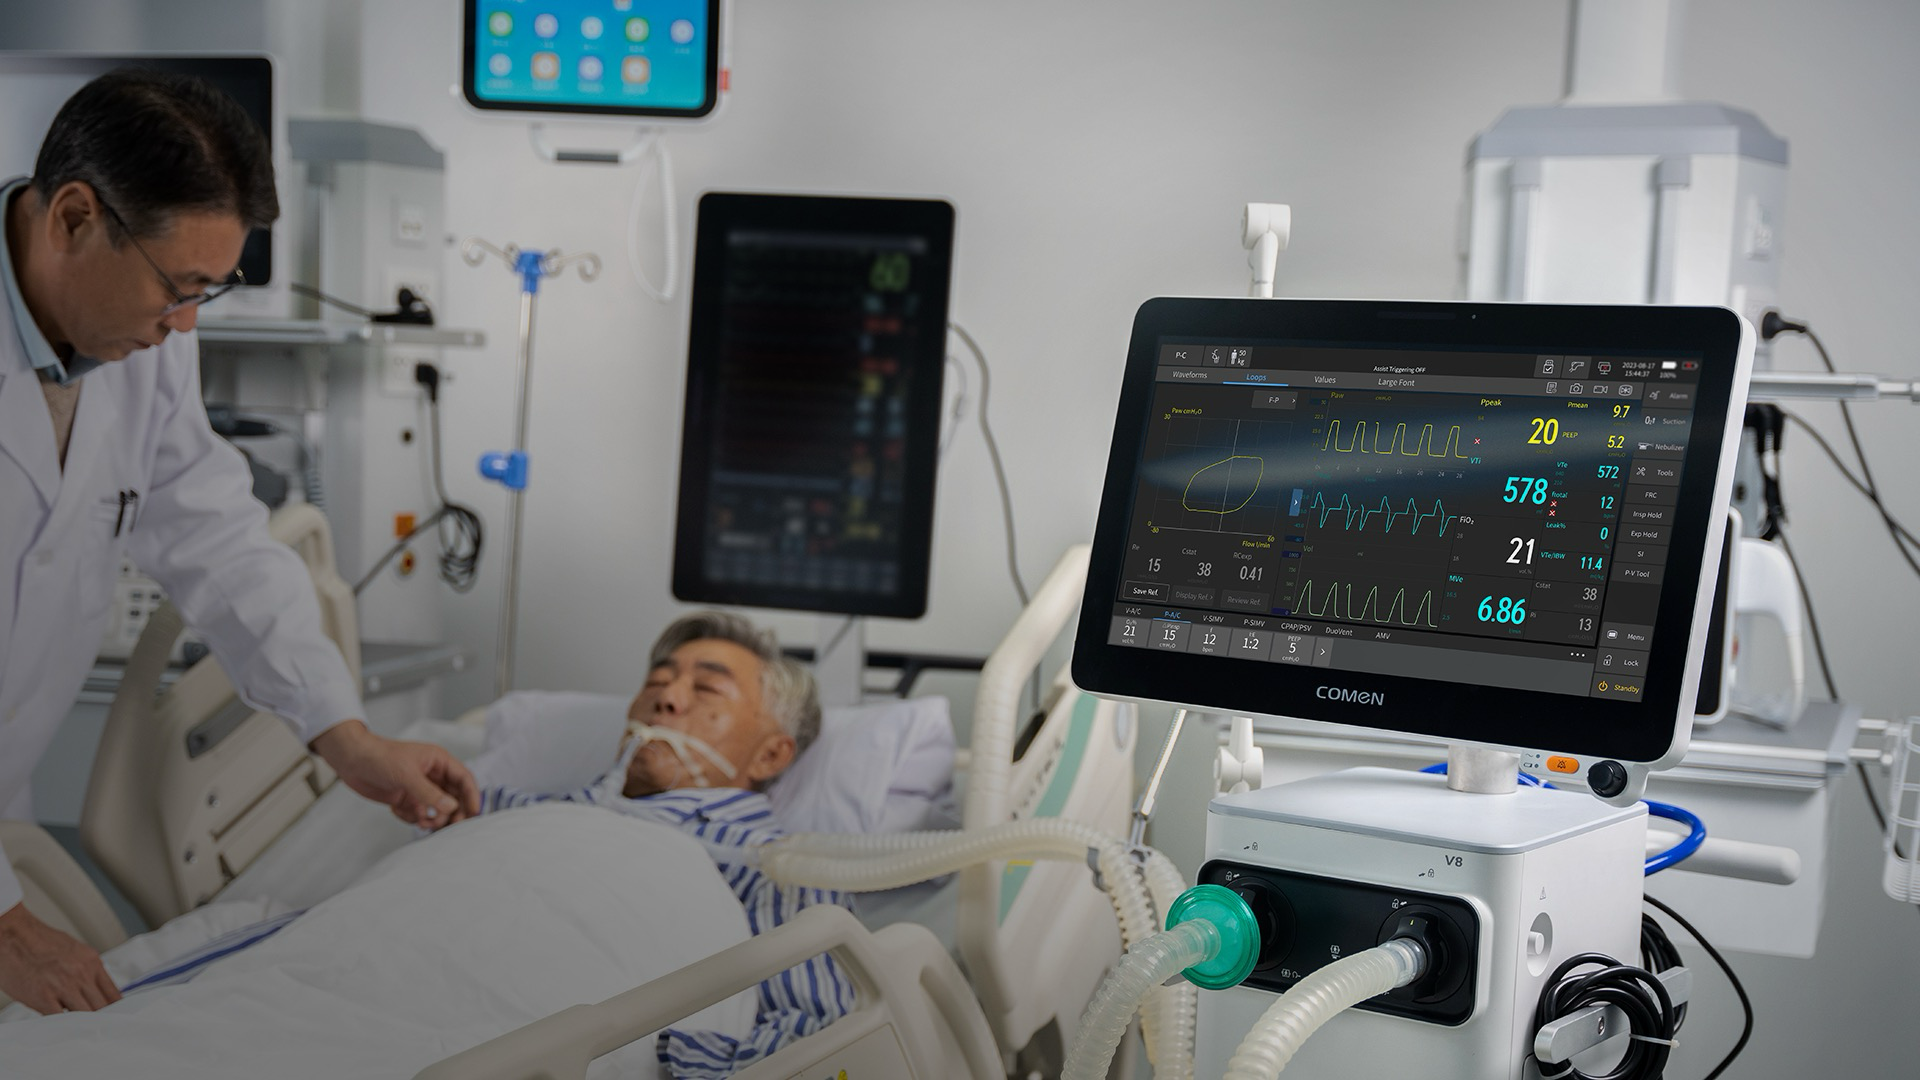
Here are three evaluation metrics I force into every contract. First: Verified Field Failure Rate (FFR) over 12 months—show me numbers, not promises. Second: Mean Time To Restore (MTTR) for critical functions—if your ventilator needs two days to be serviceable, we’re done. Third: Traceable Calibration and Sterilization Records tied to batch lots—no records, no shipment. These metrics let me compare vendors on reality, not glossy brochures. I interrupt myself: buy reliability, not rhetoric. Then I buy the support package.
I’ve made bad calls—one supplier in 2016 shipped a batch of infusion sets with a mislabeled connector; we caught it before use, but the recall cost taught everyone involved a useful lesson. Today I look for proof: test reports, field data, and a willingness to alter designs. That’s how I advise wholesale buyers and internal procurement teams. We measure, we enforce, we fix.
Final thought: if you want fewer night-shift Sharpies, insist on measurable acceptance tests, demand calibration records, and treat serviceability as part of the device’s spec. Evaluate suppliers on FFR, MTTR, and traceable sterilization. Small checklist items; big returns. COMEN